There is now a rule in the maternity units of West Yorkshire that says three minutes. If a machine monitoring an unborn baby’s heartbeat loses its signal and staff cannot get it back, an alarm has to be raised within three minutes. Not soon. Not promptly. Not at the discretion of whoever is in the room. Three minutes, and then somebody more senior has to be told.
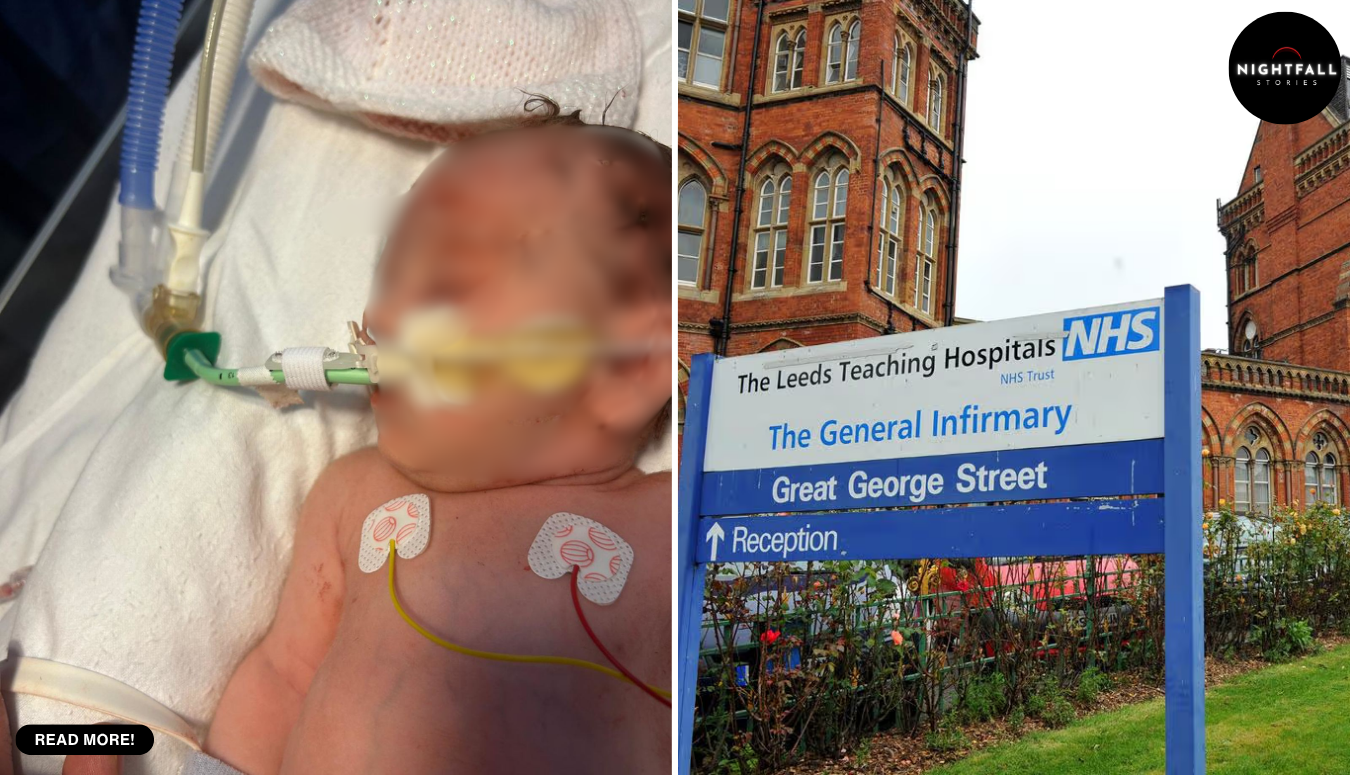
Before that rule existed there was no number at all, and in late 2024, at Leeds General Infirmary, a baby’s heartbeat went unmonitored during labour for a period the coroner later put at between 33 and 42 minutes. Her name was Delilah-Jayde Arnold. She was delivered by emergency caesarean, she never recovered, and she died seven days later. She would now be nearly two years old.
Her mother, Kelly-Marie Harris, spent two days at Wakefield Coroner’s Court last month listening to how that happened, holding a small white knitted heart. She came out of it with two things. One was the three minute rule, which is already in force across the region and did not exist when her daughter was born. The other was a finding she did not want, and the gap between those two things is what this story is actually about.
Start with the machine, because almost nobody outside a maternity unit knows what it does or how it fails. During labour, staff watch an unborn baby’s heart rate continuously, because heart rate is the only usable window onto whether the baby is coping. Contractions squeeze the womb and briefly reduce the blood, and therefore the oxygen, reaching the baby. A healthy baby absorbs that and recovers between contractions. A baby in trouble shows it in the pattern: the rate dips after a contraction and takes too long to come back, or the baseline creeps up, or the small beat to beat variation that signals a well oxygenated nervous system flattens out. Those dips are called decelerations, and a midwife reading a trace is reading them the way a pilot reads an instrument.
Usually the signal comes from a sensor strapped to the mother’s abdomen. It is non invasive and it is also fragile. Babies move, mothers move, fat and fluid get in the way, and the trace drops out. When a good reading matters enough, the alternative is a fetal scalp electrode, a small clip attached directly to the baby’s head through the cervix, which gives a far more reliable signal because it is not listening through anything.
At Delilah’s birth, the inquest heard, staff tried repeatedly to attach a fetal electrode and could not get it to work. That detail matters for a reason that is not anybody’s fault in that room: the court also heard that an alternative type of electrode was not available, because of a national procurement problem. So the clinical picture was a labour where somebody had judged that a reliable trace was needed, the reliable method would not attach, and the other reliable method was not in the building.
What follows is what the inquest called a failure to escalate. Loss of contact with a baby’s heartbeat is not itself an emergency. It happens constantly and most of the time it is resolved in seconds. The danger is that it looks identical, minute by minute, whether the baby is fine or the baby is dying. A silent monitor tells you nothing, and nothing is very easy to sit with when you are busy, because there is no alarming trace in front of you. That is the trap, and it is a human one rather than a mechanical one. The longer a gap runs, the more it feels like a technical nuisance and the less it feels like a clinical event.
The inquest heard that midwives did raise concerns. One had noted worrying decelerations earlier and escalated; another asked for more senior support. But there was no rule that converted a certain number of minutes without a heartbeat into a mandatory alarm, and so the gap ran. On the first day of evidence the figure reported in court was around 45 minutes. In his conclusion the coroner narrowed it and put it as a range, between 33 and 42 minutes before delivery, with no monitoring of the fetal heart rate and no recognition that this was in itself a risk to the baby.
Harris told the court she believes the emergency response was too slow, and that if an emergency bell had been pressed she might have reached theatre considerably sooner, which could have changed the outcome. A caesarean was eventually carried out that evening. Delilah was born in very poor condition, with a heart rate far below where it should have been, and she had seizures from the start. A pathologist concluded that her brain had not received enough oxygen around the time of birth. Her parents were told there was no brain activity. She lived a week.
Oliver Longstaff, the Acting Senior Coroner for West Yorkshire Eastern, returned a narrative conclusion, which is worth explaining because the word narrative is doing real work. An inquest is not a trial. It does not decide blame or liability, and it cannot name anyone as responsible. It answers four questions: who died, and where, when and how. For that last one a coroner can use a short form conclusion, a single word or phrase from a fixed list, natural causes, accident, suicide, and so on. Or, when none of those captures it, the coroner can write a narrative, a short factual account of the sequence of events. That is what happened here. Longstaff found that the monitoring of Delilah’s heart rate had been deficient, and that this deficiency was directly causative of the condition she was born in and from which she died.
He also said something that Harris had asked for and did not get. One of the short form options available to a coroner is neglect, and in the inquest context neglect has a narrow, demanding legal meaning. It is not the everyday sense of carelessness. It requires a gross failure to provide basic medical attention to someone in a dependent position, and a clear causal connection between that failure and the death. Gross means far beyond ordinary error. Basic means fundamental, not sophisticated. Courts have been deliberately strict about it, because a finding of neglect at an inquest carries a weight that ordinary substandard care does not.
Longstaff declined to make that finding, and his reasoning was short. You cannot find a gross failure, he said, when something is being done, however badly it is being done. Staff were not absent. They were not ignoring the labour. They were trying, repeatedly, to attach an electrode, and failing, and not escalating. In law that is deficient care. It is not nothing being done at all.
Harris said she was disappointed. That is the second injury families describe after an inquest, and it is worth taking seriously rather than treating as a technicality misunderstood. To a bereaved parent, a finding that care was deficient and directly caused a death, coupled with a refusal to call it neglect, can read as the system grading its own failure and awarding itself a pass. It is not that, legally. But the distinction is drawn on the shape of the failure rather than on its consequences, and consequences are all a parent has. Both things are true at once: the coroner applied the test correctly, and the test does not measure what Harris lost.
Where she did get something is the part that will outlast the conclusion. After Delilah’s death, Leeds Teaching Hospitals NHS Trust reviewed what happened internally and externally, and changes followed. New guidance on fetal heart rate monitoring, including the three minute escalation requirement. Changes to equipment. Changes to training and staff education. And that guidance is not confined to one hospital. It is now used across West Yorkshire maternity services, which is a region of several million people and a substantial share of England’s births.
The trust’s chief medical officer, Dr Elizabeth Garthwaite, said the trust’s thoughts remain with Harris and her family, offered its condolences, acknowledged the lasting grief, and said the trust is deeply sorry that failings in care were identified by those reviews and for the pain that has caused. That is an unusually direct acknowledgement from an English hospital trust, and it is worth recording as such, without pretending it settles anything.
Then the coroner did the thing coroners do that has more reach than any conclusion. He issued what is formally called a report on action to prevent future deaths, known from the regulation that creates it as a Regulation 28 report. The power is simple and blunt: if an inquest reveals something that creates a risk of other deaths, the coroner must write to whoever has the power to fix it and say so. The recipient is legally obliged to respond in writing within fifty six days, either setting out what they will do or explaining why they will do nothing. Coroners have used it to change car park barriers, prison observation regimes, medicine labelling and motorway signage. It is one of the few mechanisms in English public life where a single death reliably generates a written answer from an institution.
Longstaff sent his to the clinical director of the National Institute for Health and Care Excellence, the body that writes the clinical guidelines English maternity units are expected to follow. His question was essentially whether the West Yorkshire fix should be the national one: should there be a defined time limit, nationally, for escalating a loss of fetal heart rate monitoring.
That referral is live. It has not been decided, and it should not be reported as though it has. NICE will consider it the way NICE considers things, which means looking at the evidence base for a specific number rather than at the merits of one case. The question it has to answer is harder than it sounds. A rule with a number in it is a genuinely different instrument from a rule without one, and that is the intellectual heart of this story.
A guideline that says escalate promptly is unenforceable, unauditable and infinitely negotiable. Everyone agrees with it and nobody can be found to have breached it, because prompt is whatever it looked like at the time to someone under pressure. A guideline that says three minutes is a different object entirely. It can be taught in a sentence. It can be built into a machine’s alarm. It can be counted on a clock by the most junior person in the room, which means it transfers authority downward: a student midwife does not need to make a clinical judgement or win an argument, she needs to look at a watch and say three minutes, we escalate. Afterwards it can be audited from the records, and it gives anyone reviewing a case a fixed line rather than a debate about reasonableness.
The cost of numbers is that they are arbitrary at the edges and they generate false alarms. Three minutes will sometimes summon a senior clinician for a signal that returns at three minutes and ten seconds, and in a busy unit that is a real cost. Every safety rule with a number in it buys clarity by accepting some waste. The argument for doing it here is that the failure mode being guarded against is silence, and silence is the one thing human attention is worst at noticing.
None of this is happening in a vacuum. English maternity care has been the subject of a long run of published investigations, at Shrewsbury and Telford, at East Kent, at Nottingham, and in a national review, and the recurring findings across them are depressingly consistent: heart rate traces misread or not read, concerns not escalated, and a reluctance to interrupt the expected course of a labour. The Shrewsbury and Telford review concluded that more than two hundred babies might have survived with better care. Against that background, a single inquest producing a concrete, countable, regionally adopted rule is a small thing that actually bites, which is more than most of the reports can claim.
Harris has said she hopes the national guidance changes so that other families do not go through this. That is the whole of her position, and it is a narrow ask from someone entitled to a much larger one.
So here is where it stands. A rule that did not exist now exists, in a region with millions of people in it, and it exists because a woman sat through two days of evidence about the worst thing that has ever happened to her rather than letting the file close. The coroner found the care deficient and stopped short of neglect, and she has to live with that wording. The question of whether three minutes becomes the number for the whole country is sitting on a desk at NICE, waiting for a written answer.
She changed the rule for one region. She is waiting to find out whether she changed it for everyone.